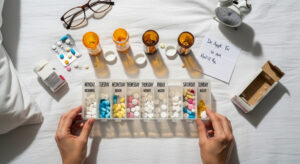
Medication reconciliation is a critical process in healthcare, and it involves comparing the medications that a patient is taking with newly ordered medications to identify and resolve discrepancies. This process is strongly recommended to be performed for patients in hospitals, clinics, nursing homes, and so on.
When Medication Reconciliation Happens
The optimal time for the mentioned process is within at least three specific time frames, within 24 hours of patient admission, during patient transfer between wards, and at the time of discharge. In some cases, one day before having an operation is also acceptable.
Building a Complete List of Current Medications
The first step in medication reconciliation is to develop a comprehensive list of all the patient’s current medications.

Medications After Hospital Discharge
This includes prescription drugs, over-the-counter medications, herbal supplements, and vitamins. The list should include the name of each medication, its brand name if needed, the dosage, frequency, route of administration, and a few more details.
This information can be obtained from the patient, relatives and caregivers, healthcare providers, medical records, medicine box, and the dispensing pharmacy. If an in-person interview is not possible, you may need to call these sources in some cases.
In this interview, you also should ask patients about special circumstances like pregnancy, breastfeeding, G6PD deficiency, alcohol consumption, smoking, liver or kidney impairment, using antibiotics within the last few months, and a history of recurrent seizures.
What to Physically Bring to the Pharmacist
We have this handwritten medication list that last discharge summary from the last time you were here two months ago. This is what they said I took, and you realize sometimes the med wasn’t done, or they just printed off something that was old. Or we have medication bottles, you open up one bottle, and it’s three different colored pills in it.
Can we start from square one? What did you take today? What did you take yesterday? What have you taken in the past week? So we can kind of work backwards and figure out what the real picture looks like. Or you get this pretty nice list that’s completely laminated, and it’s like, when did you do this? Has anything been added or taken off? Since it’s laminated, you can’t do anything with it.
Common Discrepancies Pharmacists Look For
Omitted medications are medications that they forgot to tell us about, they don’t have the bottle, it wasn’t on the list, it was just added.
Duplicate therapy is when patients don’t know if their blood pressure medication changes, they have to stop the one they were taking before, or we’ve got to titrate this down, if it’s not clearly communicated. An incorrect dose or frequency happens when it changes from twice a day to once a day, or once a day to three times a day, and patients don’t know how to find out about that change if the doctor just makes a phone call or leaves a voicemail.
Medications that are no longer taken but are still listed need to be asked about, how long ago did you stop this, is this why this looks like this, are you taking these two together. Medications prescribed but never taken are still listed, even though the medication is still in the bag and the patient decided not to take it.
Communicating the Final, Reconciled List
Communicating the reconciled list ensures that the patient is aware of the medication regimen and can help prevent medication errors. Pharmacists should provide easy-to-understand information about all medications the patient has to receive, including both the discharge prescription items and the medicines previously taken for chronic diseases such as hypothyroidism or hypertension.
We always want to bring the level down, your sugar pill, your water pill, then we spell it out to them, so we’re giving them accountability, and you find that bottle with those letters on it.
A Helpful Tool: A Household Medication List
A local fire department made a sheet with a point of contact and all the medication stuff, and it’s in a folder, and it’s on a magnet, and it sticks to the refrigerator. As a paramedic walking in on an unconscious patient, the first place you check is the refrigerator, since it has a list of drugs and also has the emergency point of contact.
What to Do With Medications No Longer Needed
Just so he’s not double-dipping, he probably needs to get rid of it, and what we don’t want him to do is flush it. You can give him one of those mail self-mail envelopes, and they have drop-off days, sometimes at local fire departments, and there is a system where you don’t have to pay postage. We can’t dispose of narcotics, but we just hand them an envelope, and they just throw it in like regular mail.